
How Do We Achieve Early Diagnosis?
Updated and Republished: Monday September 28, 2026 | Originally Published Saturday March 9, 2013
Early diagnosis of retinoblastoma is vital to save a child’s life and sight with minimally invasive therapies. But achieving early diagnosis is neither simple nor easy. WE C Hope CEO, Abby White, explores various routes to awareness and diagnosis, and how they can impact patient care.
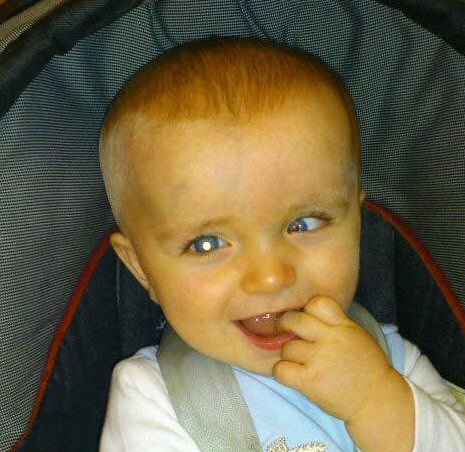
A baby has white pupil (leukocoria) in his right eye and squint (strabismus/crossed eyes) in his left eye – the two most common signs of retinoblastoma.
Retinoblastoma specialists agree that early diagnosis of eye cancer is a child’s best hope of survival, retaining some vision, or their eye. Despite the progress in developing eye salvage therapies, many children are diagnosed at a stage when removing their eye is the best treatment for survival. In many parts of the world, early diagnosis is a child’s only hope of cure.
Early detection is one of the greatest challenges facing the retinoblastoma world. Most affected families have a harrowing story to tell of white eye photos going unnoticed due to lack of awareness. They tell of doctors dismissing leukocoria and squint and other symptoms as “normal” or not listening to parental concerns and failing to refer to an ophthalmologist. Many describe being referred through multiple doctors and hospitals before a diagnosis was finally made.
All these barriers waste precious time and – for many families – very limited resources.
So what is the answer? Many solutions have been proposed, including the use of specialised imaging/photographic technologyand non-invasive mandated screening of the fundal (red) reflex. Or, simply providing parents information on signs or symptoms to be aware of and how to seek health advice. Here we consider the potential and limitations of each of these approaches.
The Retina and Retinoblastoma
Before we explore the different approaches to retinoblastoma awareness for early detection, it is important to understand the structure of the retina.
The retina is the light-sensing tissue that lines the inside of the eye. It forms about 72% of the eye’s inner lining from the optic nerve at the back to the ciliary body surrounding the iris (coloured ring) at the front. The junction of the retina and the ciliary body is called the ora serrata.
The posterior pole, encompassing the optic nerve and macula, is clearly visible on dilated eye exam. This posterior pole makes up about 2.1% of the retina and enables detailed vision.
The remaining 97.9% is referred to as the peripheral or anterior retina.
Retinoblastoma forms when genetic changes occur during normal cell division as the retinal cells continue to divide and multiply in a circular pattern from the posterior pole outwards. Tumours at the posterior pole affect central vision the most, even when they are very small. Tumours can arise anywhere on the retina, and the older the child is when they form, the further away they will be from the central vision.
Note the difference between “anterior tumour” and “anterior chamber”:
Anterior tumour refers to cancer arising in the anterior retina.
The anterior chamber is a fluid-filled space at the front of the eye between the cornea and iris. It contains aqueous humour, the clear fluid that circulates through the front of the eye.
When retinoblastoma invades the anterior chamber, the child’s life is at risk as cancer can easily spread through blood vessels to the bone marrow.
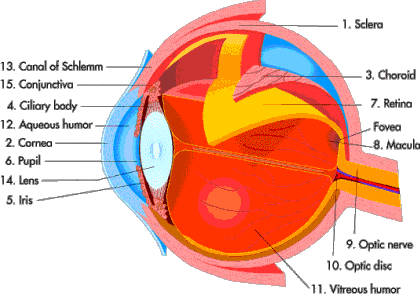
Internal structure of the eye.

Structure of the retina, which forms about 72% of the eye’s inner lining.
Mandated Fundal (Red) Reflex Test at Birth
The World Health Organization now recommends examination of the fundal (red) reflex test for all newborns. This is valuable in detecting various vision-impacting eye conditions at birth (e.g. cataract).
Retinoblastoma in newborns can be seen with a simple fundal feflex test as tumours in this age group form in the easily visible posterior pole. However, tumours may be too small to detect with this test. Tumours may form and develop as the newborn grows and develops.
Because tumours in newborns are mostly very small, they are most often found in babies with an identified risk due to retinoblastoma in a blood relative, or when they are known to carry an RB1 gene change. Babies known to be at-risk should have a full, dilated fundus examination by an eye health professional experienced with retinoblastoma, not simply a Fundal (Red) Reflex Test.
Mandated Well Child Fundal (Red) Reflex Test
There is a general belief that regular eye exams, including fundal reflex tests, performed by primary care physicians will dramatically improve early detection of retinoblastoma. However, awake eye exams, even with dilating drops, enable clear examination only of the posterior pole. No published research has documented the proportion of retinoblastoma arising from the posterior pole, but the younger the child is, the more likely the tumours will form in the posterior pole.
Small anterior tumours are usually only visible when the eye is examined under general anaesthesia. This is because the eye must be significantly manipulated to view these parts of the retina and this cannot be done on an awake child. Anterior tumours don’t cause consistent, obvious squint or white pupil in photographs or awake exams until they increase in size.
- When larger tumours reduce vision, they cause a squint.
- When larger tumours obscure the posterior pole, they cause the white pupil.
Mandated screening for retinoblastoma also relies on the primary doctor performing the fundal reflex test correctly. There is a high risk of cancer being missed on exam because
- Tumours are located in the anterior retina.
- The exam has not been done correctly.
- The child is unable to co-operate with the exam.
A “clear” exam result could give a parent false reassurance, and stop or delay their advocacy for appropriate care when they see signs the doctor is unable to observe.
Fundal reflex tests during well child exams are definitely important, but they are far from a panacea. Educating primary health workers to listen to parent and carer concerns, and refer promptly to an ophthalmologist, is likely to be far more effective in achieving early diagnosis.
We Are TLM explains why it’s important to ask for an eye exam when parents see squint, white eye glow or a painful red eye in their child.
Ocular Computerised Tomography (OCT)
Ocular computerised tomography (OCT) was introduced to monitor the eyes of newborns at risk for retinoblastoma. This screening tool can identify developing tumours before they are visible to the ophthalmologist using indirect ophthalmoscope or retinal photography.
OCT is a non-invasive method of imaging the layers of the retina and optic nerve. Imagine a layer cake with its attractive icing top, cake layers, and filling. When we look inside the eye, we see the ‘top of the cake’. With an OCT, we are able to see the individual layers of the cake, down to its individual crumbs. In the eye, the medical team can find miniscule tumours before they emerge.
OCT is set to transform early detection of retinoblastoma in babies whose risk for new tumours is known, and who are already receiving specialist ophthalmic care.
Community Eye Health Outreach in LMICs
In low and middle income countries (LMICs), community eye health outreach can play a vital role in early detection of retinoblastoma and other potentially blinding childhood eye diseases. In many rural and underserved regions, families have limited access to routine well-child care, primary doctors, cameras, smartphones, and specialist eye services. As a result, children often present with advanced, life-threatening disease.
Community screening initiatives using the fundal (red) reflex test can help bridge this gap, particularly when integrated into existing maternal and child health programs such as newborn care, immunisation clinics, and outreach eye camps. In these settings, the exam is likely to be performed by healthcare workers specifically trained in primary eye care and interpretation of abnormal fundal reflex findings.
Development of the Arclight ophthalmoscope has significantly improved the feasibility of community-based screening in resource-limited settings. Solar-powered, portable, and durable, these low-cost devices are thoughtfully designed for use in regions with limited infrastructure. Their smart technology supports training, outreach, telemedicine, and rapid referral for specialist care.
While community screening cannot detect every retinoblastoma, especially very small anterior tumours, it can identify many children earlier. They would otherwise receive no eye examination at all until disease is advanced, treatment is complex and costly, and potential for cure is remote.
Community screening alone is not enough. Eye health outreach is most effective when combined with public awareness and healthcare worker education. Recognition of early signs, parents empowered to access available eye health care, and referral pathways to specialist care work together to ensure children receive timely diagnosis and life-saving treatment.
In the following video, can you identify which findings indicate the child needs a specialist referral? Answers are shown after each image is presented – test begins at 2:00.
Symptom Information in Expectant Mother Packs
Retinoblastoma advocacy charities in several countries have successfully campaigned to include information about early signs of retinoblastoma in Ministry of Health produced materials provided to expectant parents. This simple information educates families about the signs to look for and what to do if concerned, and becomes a resource they can present to doctors to back up their concerns and request for ophthalmology referral.
This approach is complicated in a country where resources for expectant parents are developed by state or provincial health authorities, rather than by a national ministry. However, the process is no more complex than attempting to mandate regular eye exams, and with much greater impact as the information is put into the hands of the parent – the child’s key advocate.
Including information in Maternal and Child Health resources is an excellent way of giving reliable information directly to parents before their children are born. Ongoing education is also more likely as the process becomes part of an established state program, rather than relying on funding from the charity or a dedicated individual family.

Information card developed by Dr. Sandra Staffieri, Clinical and Research Orthoptist at the Centre for Eye Research Australia (CERA), and Retinoblastoma Care Co-ordinator at the Royal Children’s Hospital, Victoria.
Community Education
Community education initiatives can reach the target audience. As a rare cancer, achieving sustainable and cost-effective education is an important consideration. Cost effectiveness measures the cost of a campaign against the number of children diagnosed as a direct result of it.
Large scale community education can be achieved through promotion in commercial districts, at town fairs, and community events. A simple poster can also be very effective at infant vaccination clinics and community centres where parents gather.
Community education often relies heavily on volunteers, and is sustainable only so long as people commit their time and energy to making it happen. Awareness that relies on this kind of education is unevenly distributed, putting children’s lives and sight at risk in under-served areas.
To evaluate the impact of community education, retinoblastoma specialists would need to ask parents of affected children what prompted them to seek health advice.

KnowTheGlow poster highlighting the white pupil glow that can indicate retinoblastoma and other potentially blinding childhood eye conditions.
Media Coverage
With the increased use of social media, the cost of highlighting retinoblastoma early warning signs has become more cost effective. However, sharing individual stories is not a systematic approach to awareness, rather it is an incidental opportunity.
Targeted social media campaigns in different languages can reach key audiences around the world, such as specific age groups, parents, and photographers. The opportunities and challenges are similar to those of community education initiatives.
News media has huge capacity to help raise awareness of retinoblastoma. Many excellent stories have been published around the world, promoting awareness of white pupil in a child’s photograph, and children’s lives have been saved as a result. Sadly, many families have frustrating stories of articles not including white pupil or squint information or example photographs, reporting facts incorrectly or sensationalizing their story such that the educational impact is lost.
Social media stories and news media coverage of retinoblastoma is hugely important and a vital adjunct to systematic early detection initiatives. But they should not be relied on as the only form of national awareness. In too many countries however, this is the only route families have to spread the retinoblastoma message widely.
Developing Effective Awareness Initiatives
All these approaches have a role to play in improving early diagnosis rates. Some are more sustainable and cost effective than others. Some will catch only certain presentations of retinoblastoma. Some require specific systems to exist before they can be implemented.
A truly effective national awareness program will most likely involve a mix of approaches, defined through careful planning and development. Here are some key questions the planning team will ask in developing a long-term sustainable awareness program:
- What is needed in this country / region?
- What existing systems can we build on?
- What is the potential to improve early diagnosis?
- What is the evidence for this approach?
- What is the reach of this approach (how many children)?
- What is the anticipated cost-effect of this approach?
- How can we measure impact?
- What is the potential for long term sustainability?
One Retinoblastoma World is a prime example of collaboration. Every conference program includes panels and open-floor discussion about awareness, screening, referral, and early diagnosis initiatives around the world. They bring together parents, survivors, advocates, researchers, and retinoblastoma specialists to share real-world experiences, research findings, and practical solutions from diverse communities and healthcare settings.
We have explored many aspects of early diagnosis, including:
- Public awareness campaigns.
- Community eye screening programs.
- Healthcare worker education.
- Patient-led advocacy.
- Low-cost diagnostic technologies.
- Improving referral pathways in both high and low resource settings.
Our many discussions highlight that no single approach works everywhere. Instead, sustainable progress depends on collaboration, adapting strategies to local healthcare systems and cultures, and learning from successful initiatives across the global retinoblastoma community.
The One Rb World sessions also emphasise that families and survivors are key partners in developing effective early detection initiatives. Their lived experience provides vital insight into the barriers that delay diagnosis, the messages that resonate most strongly with diverse communities, and the supports families need to act quickly when concerns arise.

Awareness is One Part of the Retinoblastoma Triangle
Early diagnosis is only the beginning and one part of the challenge in retinoblastoma care. Systems must also be in place to effectively refer and treat children, and support families, after early detection. These include:
- Referral to an ophthalmologist who has the capacity to confirm diagnosis and expertise to treat retinoblastoma.
Early detection becomes meaningless if a child is referred to a non-specialist hospital, or none at all. This can happen when the diagnosing doctor doesn’t know where to send them for expert care, or encounters barriers in the referral process.
- Access to treatment in the country where the child lives, and if not, the capacity for supported medical transfer.
Early detection is a hollow success if resources and expertise are not available to save at least one eye of a bilaterally affected child, when safe to do so.
- Treatment options based on clear evidence of value, risk to the whole child, and the burden of the chosen treatment.
Timely diagnosis is squandered when eye-salvage therapy puts life at risk. When removal of an eye with advanced disease is delayed and an otherwise curable child must fight for their life, or worse, lose their life that may have been saved.
- Comprehensive family support throughout referral, diagnosis, and treatment.
Early detection is futile if a child is unable to access appropriate life-saving care due to lack of financial, practical, and emotional support for the family.
Early diagnosis is a victory diminished if months or years of unsupported therapy have long-term negative effects on psychological health. The impacts of treatment trauma may remain with the child and family throughout life.
Awareness is the key starting point on the road to sight-saving care and cure. But it is not a universal remedy to the challenges we face in bringing these opportunities to children.
Our global community has much work to do. Together, we can improve timely diagnosis along with sustainable evidence based medical care, and compassionate practical family support to ensure complete care for the child their entire family.
Thank you for joining us on this journey!
Learn More About the Signs of Retinoblastoma

When ‘Something’ Looks the Same As ‘Nothing’ – learn more about strabismus, leukocoria and childhood eye cancer with this great article from Dr. Sandra Staffieri.
About the Author
Abby’s father was diagnosed with bilateral retinoblastoma in Kenya in 1946. Abby was also born with cancer in both eyes. She has an artificial eye and limited vision in her left eye that is now failing due to late effects of radiotherapy in infancy.
Abby studied geography at university, with emphasis on development in sub-Saharan Africa. She co-founded WE C Hope with Brenda Gallie, responding to the needs of one child and the desire to help many in developing countries. After receiving many requests for help from American families and adult survivors, she co-founded the US chapter to bring hope and encourage action across the country.
Abby enjoys listening to audio books, creative writing, open water swimming and long country walks.

You May Also Like…
“Have We Spoken Before?” Same Retinoblastoma Diagnosis Story, Different Parents…
Many families tell of delayed pathways to care when their child is diagnosed with eye cancer. Orthoptist and retinoblastoma care coordinator, Sandra Staffieri, and leukocoria awareness advocate, Megan Webber, are frustrated by the repeated stories and their negative patient impacts. They explore why these delays continue, some efforts to overcome the challenges, and where they find hope for the future.
Eye of the Storm: the impact of ‘not knowing’ on mental health
If In Doubt, Check It Out: Common and Not-So-Common Signs and Symptoms of Retinoblastoma
Breaking Barriers to Early Diagnosis: Revisit a Year of Action
A Global Call to Action: Early Detection and Advocacy at One Rb World 2024 Day Three | Page 1




Leave a Reply
Want to join the discussion?Feel free to contribute!